A Quick Look at Obstetric Anesthesia Care Part 2: Caesarean Deliveries
/Caesarean deliveries are among the most common major surgeries in Ontario. They’re also the only ones where the patient is routinely awake, aware and talking, and that technically involves two patients. All of this adds up to an experience that, while performed around 50,000 times a year in Ontario, is always unique and special.
It’s also a procedure that’s often misunderstood, especially when it comes to the anesthesia care used during caesarean deliveries.
With this form of birth becoming increasingly common—in Ontario, it has crept up from around 29% of births in 2010 to around 35% in 2023—we wanted to take a moment to share a patient-friendly look at what exactly “anesthesia care” means during a caesarean delivery.

As we discussed in our earlier article on obstetric anesthesiology and epidurals, our members’ goal is clear: Keep both patients comfortable, safe, and alive. The added surgical element of a caesarean delivery takes this goal up a notch, but thanks to their years of training, Ontario’s anesthesiologists are more than prepared to provide the expertise and reassurance patients need.
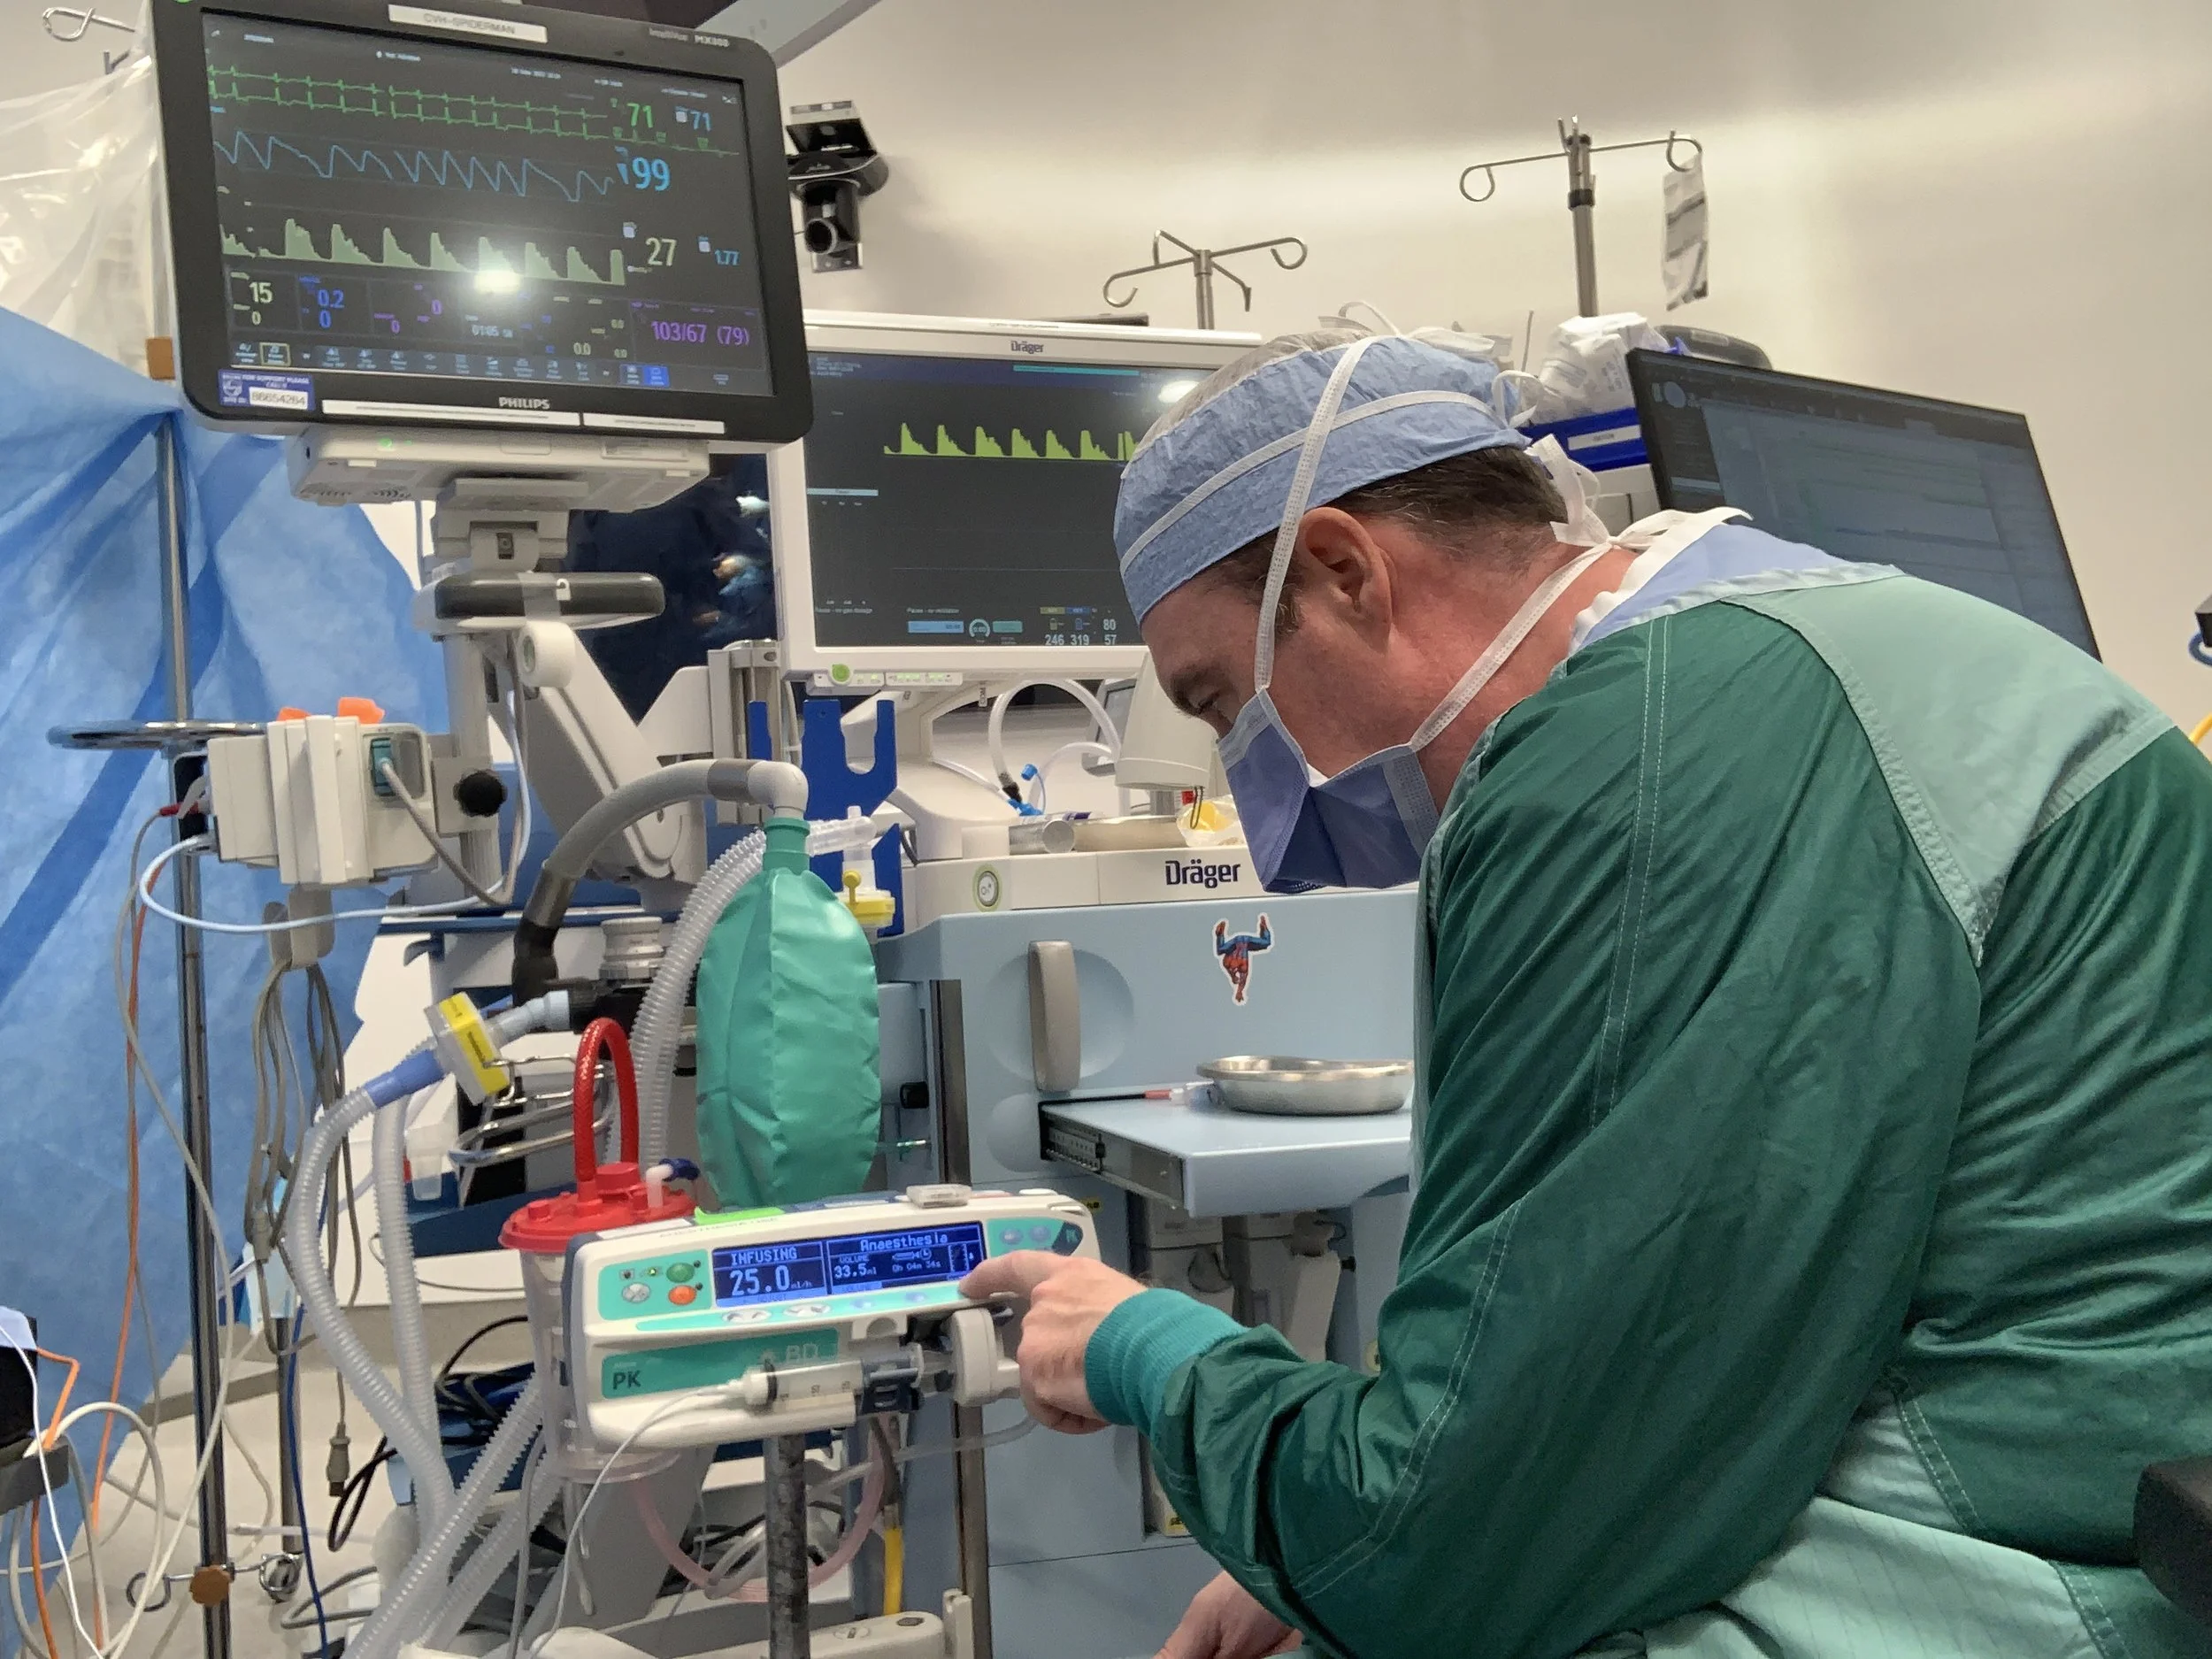
During a caesarean delivery, which can take anywhere from 45 to 90 minutes, the anesthesiologist consistently monitors and maintains vitals such as blood pressure and heart rate, provides pain relief, and is immediately on hand to provide additional supports.
But that’s not all they’re doing. “Much of our role involves direct human connection. While medications can help with anxiety, we often rely on our words, tone, and presence to provide reassurance,” says Dr. Daniel Cordovani, a staff anesthesiologist at Hamilton Health Sciences and a professor at McMaster University, where he is also the Associate Chair of Education and, until recently, the school’s OB Anesthesia Fellowship Director.
Since anesthesiologists are usually positioned near the patient’s head, they can easily answer questions and provide verbal encouragement and comfort. “We help explain what’s happening, what sensations are normal, and what to expect next. That real-time communication can make a big difference in how safe and supported they feel,” explains Dr. Cordovani.
Types of Anesthesia Care Available
While there are many different types of anesthesia, the kind administered during a caesarean delivery is usually a spinal anesthetic, explains Dr. Ron George, professor at the University of Toronto and the Director of Obstetric Anesthesia at Toronto’s Mount Sinai Hospital, home to Canada’s largest and most comprehensive academic obstetrics program.

“It is a single injection in the lower back that provides rapid, dense numbness while the patient remains awake,” he explains. This technique lasts for hours and is known for its predictability and reliability, making it the go-to for planned caesarean deliveries.
Spinals are a form of neuraxial anesthesia, a class that includes epidurals. Unlike a spinal, where a catheter is not usually used, with an epidural, a small tube is temporarily placed into the back to allow for medication to be administered for as long as needed.
In cases where a patient who attempted a vaginal birth with an epidural is escalated to a caesarean delivery, that epidural can often be used to administer the stronger medication (known as a “top-up”) needed to keep the patient comfortable during their surgery.
Some caesarean deliveries may use a combined spinal-epidural (CSE), which combines the quick onset of a spinal with the flexibility of an epidural.
Explains Dr. Cordovani, “Sometimes we choose an epidural or CSE even for a planned caesarean, especially if we anticipate a longer or more complex surgery, since it allows us to extend the anesthesia if needed.”
Ironically, the least used form of anesthesia for caesarean deliveries is probably the best-known type of anesthesia care: General anesthesia, which is only used in around five percent of caesarean deliveries. Even in emergencies, this fastest-acting option is only used 15 percent of the time. This is in part because it renders patients completely unconscious and prevents them from being present during and immediately following the birth.
Also, while general anesthesia is incredibly safe, pregnancy does slightly raise its risks. “For these reasons, it is typically reserved for urgent situations or when neuraxial anesthesia isn’t feasible or effective,” explains Dr. George, adding, “While general anesthesia isn’t the usual plan, many patients have very positive outcomes.”
In addition to the above techniques, additional pain control may be used following surgery. This involves injecting local anesthetic into the abdominal wall to help reduce post-operative pain and is most used following general anesthesia.
Which of these approaches is used depends on various factors. “Patients generally have meaningful input into their anesthesia care, within the bounds of what’s safest for them and their baby,” says Dr. George.
Spinal anesthetic is usually recommended due to its reliability. However, patients can always discuss with their health-care team their preferences around their desired level of awareness, as well as other factors including partner presence, plans for immediate skin-to-skin contact, and how the experience is structured, all of which may impact the type of anesthetic used.
“If there are specific concerns (such as anxiety, prior experiences, side effects), the anesthesia plan can often be tailored accordingly,” explains Dr. George, who notes that while the core technique is guided by safety and predictability, the overall experience is increasingly collaborative and patient-centred.

Patients who undergo general anesthesia can sometimes feel as if they “missed out” on the baby’s birth, but Dr. George says, “You didn’t miss anything by choice; general anesthesia is typically used for clear medical reasons, often to ensure the safest and fastest delivery.”
Dr. George notes that for some patients who undergo general anesthesia, it may be beneficial to have a member of their health-care team debrief them on the whole experience. Additionally, “If you’re planning future pregnancies, it’s also reasonable to discuss options ahead of time with an obstetric anesthesiologist, as many patients can have neuraxial anesthesia next time.”
It’s also important to acknowledge that sometimes, despite everyone’s best efforts, things don’t quite go as planned. “If the experience felt unexpected or difficult, it’s okay to talk about it with your care team or postpartum supports, because processing the birth experience is an important part of recovery too,” explains Dr. George.

The increase in Ontario’s rate of caesarean deliveries is part of a worldwide trend resulting from various factors, including an older, more medically complex population, changes in practice patterns and risk tolerance, and the fact that having one caesarean delivery increases the odds of having future caesarean deliveries. This means that a growing percentage of obstetric anesthesiology will focus on providing anesthesia care during caesarean deliveries.
Ontario’s anesthesiologists are ready to deliver this care with skill, confidence, and compassion.
Says Dr. Cordovani, “It can be a demanding part of the job, but it’s also incredibly rewarding, as we help guide patients through one of the most important moments of their lives.”